
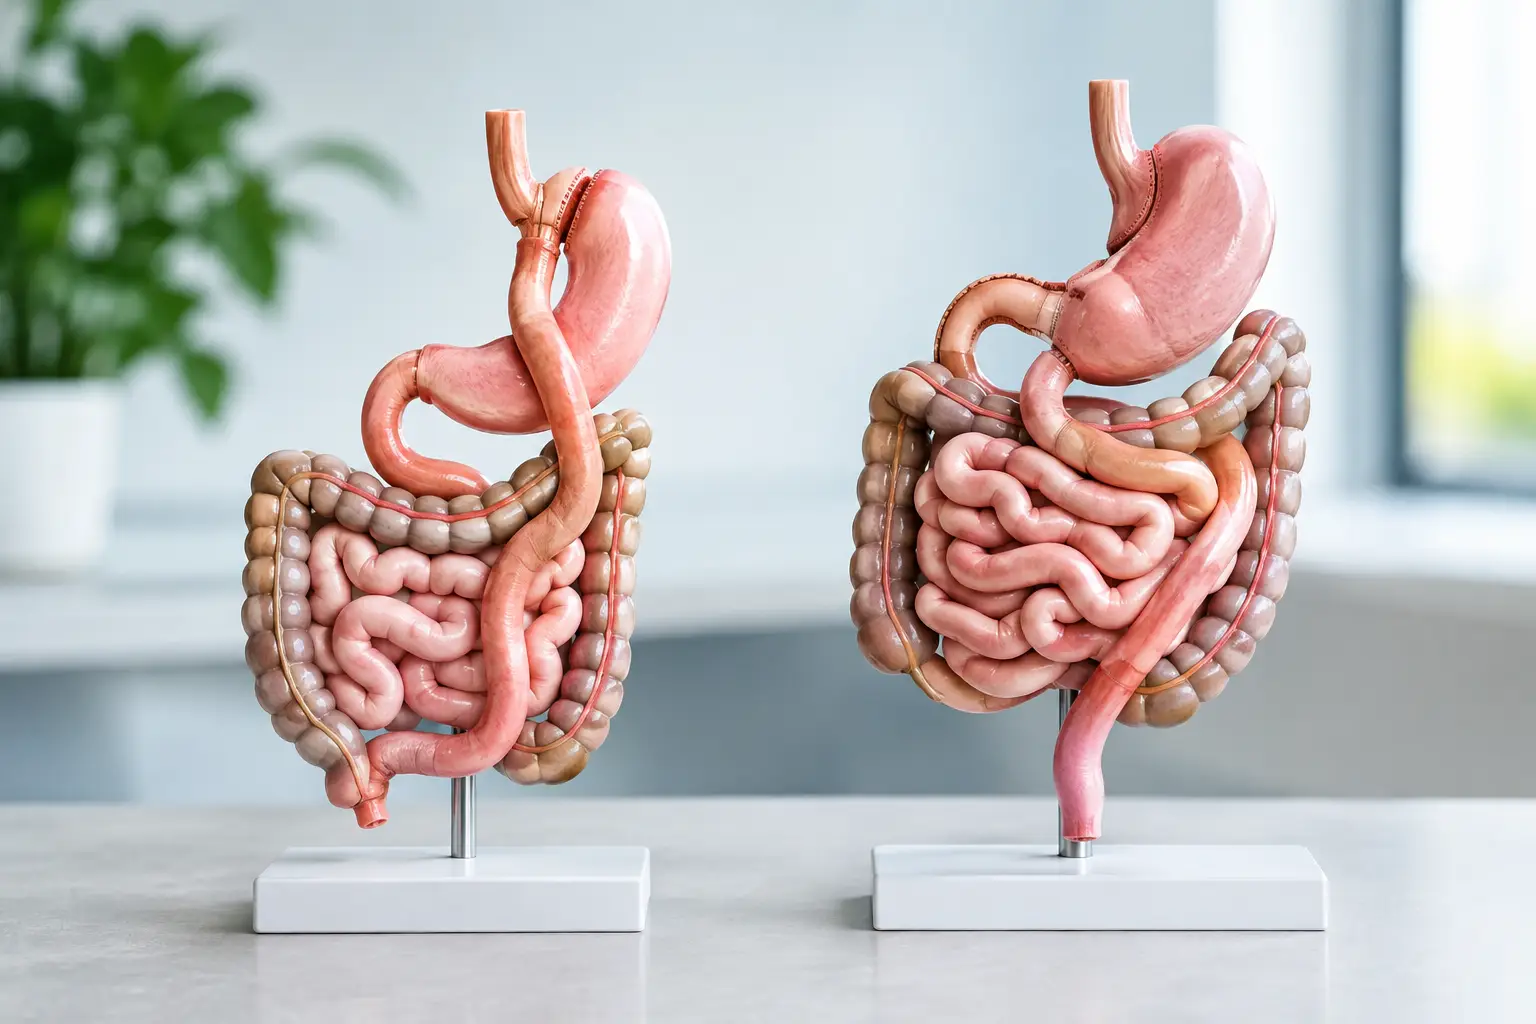

A procedure name can sound like the answer when you have spent years trying to lose weight, manage hunger, or live with conditions linked to obesity. Yet duodenal switch versus bypass is not a simple contest. Both operations can be life-changing, but they work differently, demand different levels of lifelong nutritional care, and suit different clinical situations.
The right choice should come after a detailed conversation with an experienced bariatric surgeon who understands your medical history, weight-loss goals, eating habits and ability to maintain follow-up. Your coordinator can make travel and hospital arrangements feel straightforward, but the procedure itself must always be chosen for clinical reasons – never because it is fashionable or promises the quickest result.
Duodenal switch versus bypass: the key difference
Gastric bypass and duodenal switch are both metabolic and bariatric operations. Each reduces the amount of food you can comfortably eat and changes how food moves through the small bowel. Those intestinal changes can improve hormones involved in appetite, blood sugar and metabolism.
A standard Roux-en-Y gastric bypass creates a small stomach pouch and reroutes part of the small intestine. Food bypasses the rest of the stomach, the first part of the small bowel and a section of the intestine where some calories and nutrients would normally be absorbed.
Duodenal switch is a more complex family of procedures. In its traditional form, it combines a sleeve gastrectomy with a more substantial intestinal bypass. Variations exist, including single-anastomosis approaches, so it is essential to ask exactly which operation a surgeon is recommending rather than relying on the broad label alone.
The practical distinction is this: duodenal switch usually creates a greater degree of malabsorption than gastric bypass. That may produce more weight loss and stronger metabolic effects for some people, but it also raises the long-term need for supplements, blood monitoring and careful food choices.
Weight loss and metabolic results
Both procedures can lead to significant and durable weight loss when paired with long-term dietary, activity and follow-up changes. Neither is a shortcut, and neither removes the need to build a new relationship with food.
On average, duodenal switch tends to produce greater weight loss, particularly for people starting at a very high BMI or those with severe obesity-related health risks. It can also be particularly effective for improving type 2 diabetes, high cholesterol and other metabolic concerns. That potential benefit is one reason surgeons may discuss it when a sleeve alone is unlikely to provide enough metabolic change.
Gastric bypass also has a strong evidence base for weight loss and improvement in type 2 diabetes, reflux in many patients, high blood pressure and sleep apnoea. It is often considered a balanced option: powerful enough to deliver meaningful metabolic change, while generally carrying less malabsorption than a full duodenal switch.
Results vary more than online averages suggest. Starting weight, diabetes duration, medications, mobility, food tolerance, alcohol intake, follow-up attendance and the consistency of your nutritional plan all matter. A surgeon should explain what is realistic for your individual starting point, rather than offering a guaranteed number on the scales.
Who may be suited to each procedure?
A bypass may be considered for patients who need substantial weight loss and have troublesome acid reflux, particularly if reflux is unlikely to improve with a sleeve. It may also be used as a revisional option after another procedure, depending on the reason for revision and the anatomy involved.
Duodenal switch may enter the discussion when a patient has a very high BMI, significant metabolic disease, or a history suggesting that the strongest weight-loss operation may be clinically appropriate. It is not automatically the best choice for every person at a higher weight. The ability to commit to intensive, lifelong nutritional monitoring is central to the decision.
Your medical history can change the picture. Existing bowel disease, liver problems, anaemia, osteoporosis risk, previous abdominal surgery, medication requirements and plans for pregnancy all deserve a careful review. So do practical realities: can you arrange regular blood tests once home, obtain prescribed supplements consistently, and contact a clinical team promptly if symptoms arise?
The nutritional commitment is not the same
All bariatric surgery patients need lifelong vitamin and mineral supplementation, routine blood tests and protein-focused eating. After either procedure, you will work through staged eating – usually liquids, then purées, soft foods and eventually structured solid meals – according to your surgeon and dietitian’s instructions.
After gastric bypass, common nutritional concerns include iron, vitamin B12, folate, calcium and vitamin D. Supplements are not optional simply because you feel well. Deficiencies can develop gradually and may affect energy, mood, nerves, bone health and blood counts before symptoms become obvious.
After duodenal switch, the requirements are more demanding. In addition to protein, patients may need closer attention to fat-soluble vitamins A, D, E and K, as well as iron, calcium and other nutrients. Blood results must be reviewed regularly and supplements adjusted by a qualified clinical professional. Skipping this care can have serious consequences.
Bowel changes can also be more noticeable after duodenal switch. Some patients experience more frequent stools, stronger odour, wind or loose bowel movements, especially when eating higher-fat foods. These effects are manageable for many people, but they should be discussed honestly before surgery, particularly if work, travel or confidence in social settings is a concern.
Risks, recovery and everyday life
Every operation carries risks, including bleeding, infection, blood clots, leaks and complications related to anaesthesia. The complexity of duodenal switch can mean a different risk profile and often a more intensive nutritional follow-up plan. Gastric bypass has its own procedure-specific risks, such as internal hernia, marginal ulcers and dumping syndrome.
Dumping syndrome can occur after bypass when food, particularly sugary food, moves too quickly into the small intestine. It may cause sweating, palpitations, cramps, dizziness or diarrhoea. For some people, the unpleasant response helps reinforce lower-sugar eating. For others, it takes time and support to learn which foods and portions trigger symptoms.
Recovery is not just about the hospital stay. The first weeks require rest, hydration, prescribed injections or medicines where advised, gentle walking and close adherence to the dietary stages. Returning home does not end the process. Reliable aftercare should include clear guidance on warning signs, scheduled check-ins and a plan for sharing relevant information with your GP or local healthcare team.
For patients travelling to Turkey, the practical side should be organised around safety rather than speed. That means pre-operative assessment, appropriate hospital observation, clear discharge instructions, airport transfers that do not add unnecessary strain, and a realistic plan for flying home. Bridge Health Travel coordinates these steps so patients and accompanying family members know what happens before, during and after hospital care.
Questions worth taking to your consultation
A good consultation should leave you better informed, not pressured. Ask which exact procedure is being proposed and why it is more suitable than the alternatives. Ask how your reflux, diabetes, medications and previous surgery affect the recommendation.
You should also ask what blood tests are required for life, which supplements you will need, who will review your results after you return home, and what symptoms require urgent medical advice. If revisional surgery is being discussed, ask what caused the previous procedure to fall short and whether the new operation addresses that specific issue.
Finally, ask about the support that surrounds surgery. A highly skilled operation matters enormously, but so do dietetic guidance, responsive coordinators, regular follow-up and an honest plan for the difficult moments that can arise months or years later.
Choosing with the long term in mind
The best operation is not necessarily the one associated with the largest average weight loss. It is the operation whose benefits, risks and lifelong responsibilities fit your health needs and your capacity for follow-up. For one patient, that may be gastric bypass with its established balance of metabolic benefit and nutritional demands. For another, duodenal switch may offer the stronger intervention their clinical picture requires.
Give yourself permission to ask questions until the recommendation makes sense. A confident decision comes from understanding not only what surgery can change, but also the daily care that protects your health long after the weight begins to come off.





